Appointments, clinician availability and the exact services offered should be confirmed with the hospital team.
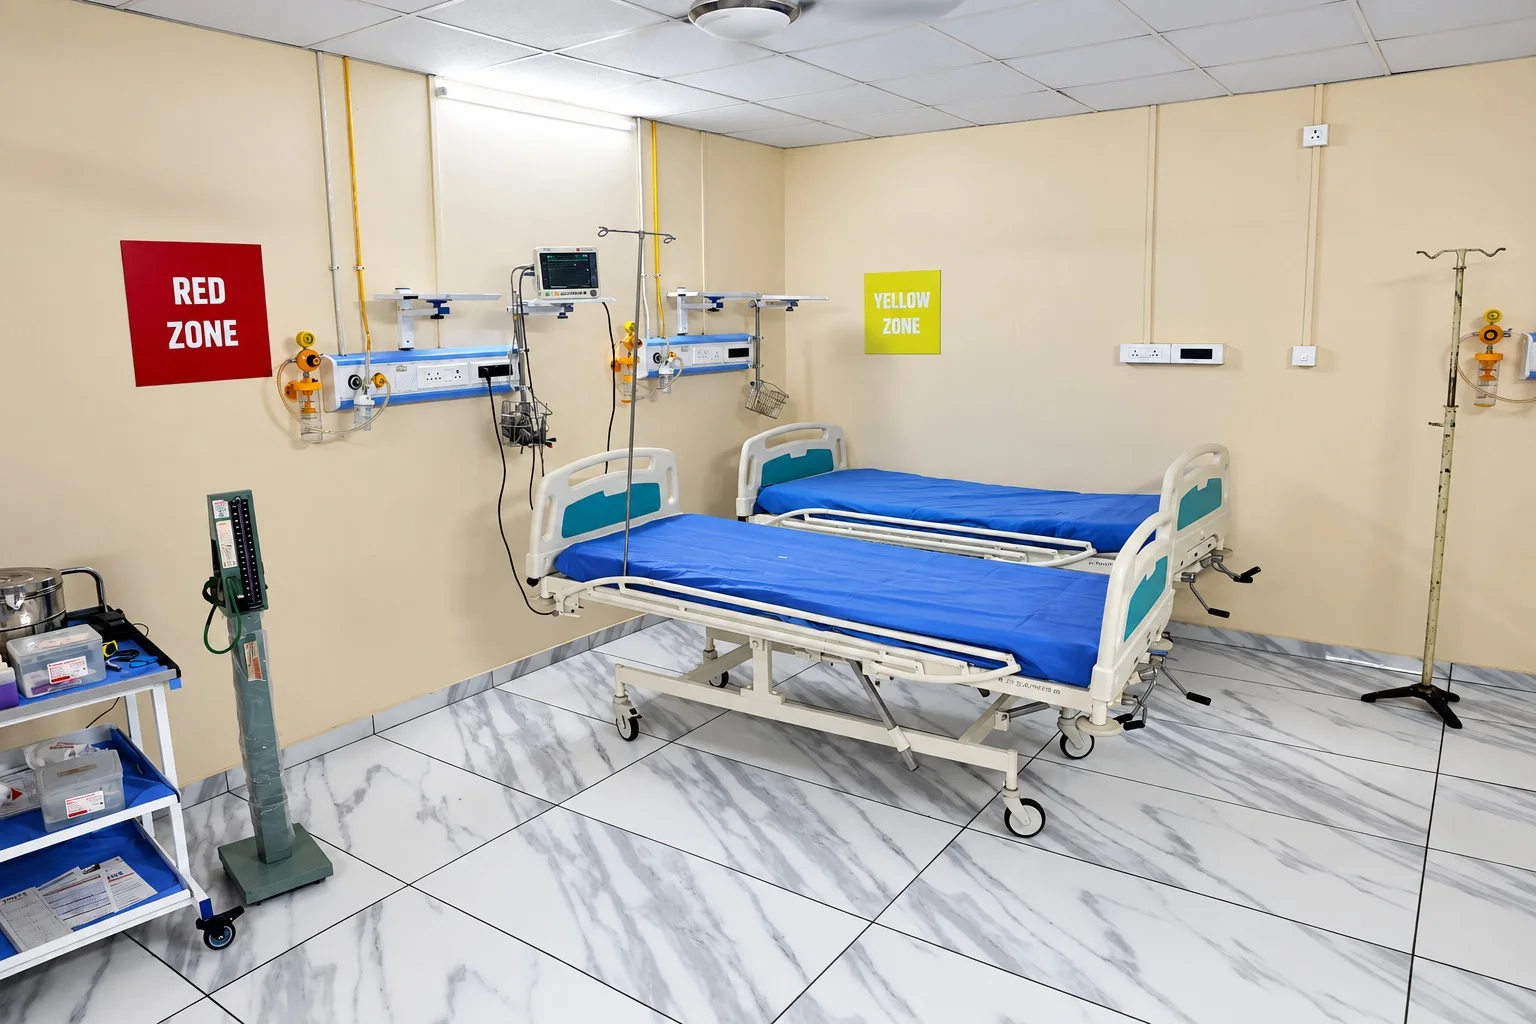
Hospital photograph. Specific care and equipment depend on the service and clinical plan.
Service overview
Discuss your concern with the clinical team
The General Surgery department at Deccan Malti Hospital handles the bread-and-butter surgical needs of the community — hernia, gallbladder stones, appendicitis, piles and fissures, lumps and swellings, and abdominal emergencies — alongside pre- and post-operative care for the hospital's other specialities. Led by Dr. Prithviraj C. Patil, a general surgeon with more than 40 years of experience, the department's philosophy is straightforward: operate when surgery is the right answer, explain it honestly, and see the patient safely through recovery.
This educational page does not diagnose a condition or replace assessment and advice from a qualified clinician.
How the consultation may help
Most people meet a general surgeon with a mixture of pain and anxiety — a groin swelling that has been ignored for months, gallstones found on a sonography done for something else, or severe abdominal pain in the middle of the night. The first job of a good surgeon is to remove the uncertainty: what exactly is the problem, does it need an operation, and what happens if you wait.
At this department, you will get a direct answer. Some findings — small asymptomatic hernias in unfit patients, tiny gallbladder polyps — are honestly advised observation. Others, like a symptomatic gallbladder or an obstructed hernia, are clearly surgical, and delay carries real risk.
Experience matters in these judgement calls. With more than four decades of surgical practice, Dr. Prithviraj C. Patil brings precisely that: the confidence to advise surgery when needed, and the equal confidence to advise against it.
Concerns that may be assessed
The examples below are general information, not a self-diagnosis checklist. A clinician decides what assessment is appropriate.
Hernia
A weakness in the abdominal wall letting contents push out — commonly in the groin or near the navel. Hernias do not heal on their own; surgical repair is the definitive treatment, and timely repair avoids emergency obstruction.
A hernia that becomes painful, hard and irreducible, especially with vomiting, is an emergency.
Gallbladder Stones
Stones causing upper abdominal pain, bloating or pain after fatty meals. Symptomatic stones are treated by laparoscopic gallbladder removal; silent stones may simply be observed.
Severe right-upper-abdomen pain with fever and vomiting needs urgent evaluation.
Appendicitis
Inflammation of the appendix starting as vague central pain that shifts to the right lower abdomen, with nausea and fever. It is a surgical emergency — timely appendectomy prevents rupture.
Do not take painkillers and wait overnight with suspected appendicitis; seek immediate care.
Piles, Fissure & Fistula
Common anorectal conditions causing bleeding, pain or discharge. Many respond to dietary and medical measures; procedures are reserved for persistent or advanced disease.
Any rectal bleeding after 40, or bleeding with weight loss, needs proper evaluation before assuming it is piles.
Lumps, Swellings & Abscesses
Lipomas, sebaceous cysts, breast lumps and abscesses. Most are minor day-care procedures; some lumps need biopsy to be certain of their nature.
A lump that is hard, fixed, growing or associated with skin change should be examined without delay.
Thyroid & Breast Evaluation
Neck swellings and breast lumps are assessed clinically and with imaging; surgery is offered when indicated, with biopsy guidance where the diagnosis is uncertain.
Any new breast lump, nipple discharge or skin change merits prompt surgical consultation.
Symptoms to discuss
Describe what you notice, when it started, how it has changed and how it affects everyday activities. Seek urgent care for severe or sudden symptoms.
A groin or abdominal swelling that appears on standing or straining
Upper abdominal pain after meals, especially fatty food
Abdominal pain that is severe, persistent or localising to one area
Bleeding, pain or a lump at the anal region
Any new lump in the breast, neck or under the skin
A wound that is not healing, or recurrent pus discharge
Assessment and investigations
General surgical diagnosis relies first on examination — an experienced clinical assessment often identifies a hernia, appendicitis or anorectal condition before any test. Ultrasound sonography is the standard first imaging for gallbladder and abdominal complaints.
Blood tests assess infection, organ function and fitness for anaesthesia. Where diagnosis is uncertain — a breast lump, a thyroid swelling, persistent bleeding — targeted imaging or biopsy is advised, and the reasons are explained.
Before any planned operation, a pre-anaesthesia check-up evaluates your heart, lungs, sugar and medicines so that surgery proceeds with risk properly understood and minimised.
Possible care options
Wherever suitable, laparoscopic (keyhole) techniques are used — for gallbladder removal, appendectomy and many hernia repairs — offering smaller wounds, less pain and faster return to normal activity. Open surgery remains the right choice in certain situations, and the reasons are explained when it is recommended.
Day-care and short-stay procedures are planned where safe: many hernia repairs, lump excisions and anorectal procedures allow patients to return home the same or next day.
Post-operative care is taken as seriously as the operation: pain control, wound care instructions, diet progression and a scheduled follow-up for wound check and report discussion.
What to discuss with the team
Led by a general surgeon with 35+ years of clinical experience
Honest advice — surgery recommended only when it is genuinely the right treatment
Laparoscopic techniques where suitable for faster recovery
Structured pre-operative assessment and post-operative follow-up
Multi-speciality backup within the hospital for patients with other medical conditions
A possible care pathway
Consultation
Clinical examination and review of any existing reports.
Investigations
Ultrasound or blood tests where needed; diagnosis explained clearly.
Decision & planning
Surgical vs non-surgical options discussed; pre-anaesthesia check-up for planned surgery.
Procedure
Laparoscopic or open surgery as appropriate, with day-care planning where safe.
Recovery & follow-up
Wound check, report discussion and return-to-activity guidance.
Preparing for a visit
All previous reports — sonography, blood tests, discharge summaries
Complete medicine list, especially blood thinners and diabetes medicines
Fasting instructions given at booking — follow them strictly before surgery
Insurance documents and ID proof for planned admission
One attendant to accompany you on the day of the procedure
Loose, comfortable clothing for after the procedure
Follow-up and recovery
Recovery after laparoscopic surgery is usually quick — most patients walk the same evening, resume light home activity within days and office work in one to two weeks. Open surgery and larger procedures need proportionally longer, with clear guidance given at discharge.
Wound care is simple but important: keep it clean and dry as instructed, watch for redness or discharge, and attend the scheduled suture-removal or review visit.
After hernia repair, heavy lifting is restricted for a defined period — typically 6–12 weeks depending on the repair. Following this advice is the best insurance against recurrence.
Deciding whether surgery is the right next step
A surgical consultation evaluates the concern and considers whether an operation could provide a meaningful benefit. The discussion may include examination, test results, prior treatment, overall health and personal goals. Seeing a surgeon does not guarantee that surgery will be recommended; observation, further testing or non-operative care may be considered.
Ask what problem the proposed operation addresses, what other options exist, the expected benefits and material risks, and what could happen if you wait. Confirm whether the recommendation is time-sensitive and which findings support it. You can ask for time to consider the information or seek another opinion.
Pre-operative assessment and practical planning
Before planned surgery, the team may review your health history, medicines, allergies, previous anaesthesia, test results and support needs. Tell them about new illness, infection, pregnancy or possible pregnancy, diabetes and blood-thinning medicines. The exact pre-operative checks depend on the procedure and individual health.
Follow the written instructions about food, drink, medicines, arrival time, transport and who should accompany you. Ask whom to contact if you become unwell before the procedure or are unsure about a medicine. Do not rely on instructions from a previous operation or another hospital.
Consent, recovery and contact after discharge
Before consenting, make sure you understand the procedure name, intended result, alternatives, possible complications, anaesthesia discussion and follow-up. Ask what recovery may involve and what support could be needed at home. A signed form should follow a clear conversation; ask for explanation whenever something is unclear.
At discharge, confirm wound care, activity, medicines, follow-up and urgent warning signs. Ask which number to call if the plan is unclear or a symptom changes. Severe pain, heavy bleeding, collapse, breathing difficulty or rapid deterioration needs urgent care; use emergency services for an immediate emergency.
Preparing for a surgical consultation
Bring the referral, reports, prior treatment details and a list of current medicines and allergies. Write down when the problem began and what has changed. If another clinician has recommended a procedure, bring the recommendation and ask the surgeon to explain whether it applies to your circumstances.
Consider bringing a support person if you want help remembering information. Decide in advance which questions are most important, such as the goal of surgery, alternatives, recovery and timing. Ask for the answer in plain language and take notes when the plan is discussed.
Managing uncertainty before a procedure
Some decisions require additional tests or time to understand the risks and benefits. Ask which information is still missing, when it should be available and whether waiting is safe. The surgeon can explain how urgent the decision is based on your findings.
If you have concerns about anaesthesia, pain, cost, work or caregiving, raise them before scheduling. The care team can explain which issues can be planned for and which may affect the recommendation. Do not feel pressured to agree before you understand the proposed care.
Patient questions
Frequently asked questions about General Surgery
These general answers support a conversation with a qualified clinician; your care plan depends on your individual situation.
Can a hernia be cured without surgery?
No. Belts and medicines may reduce symptoms temporarily, but the defect in the abdominal wall remains and usually enlarges. Surgical repair is the only definitive treatment, and planned repair is far safer than emergency surgery for a stuck hernia.
My sonography shows gallstones but I have no pain. Is surgery needed?
Silent gallstones often need no operation and can be observed. Surgery is advised when stones cause symptoms or complications. Your surgeon will explain which category you fall into.
Is life normal after gallbladder removal?
Yes. The gallbladder stores bile but is not essential. Most people eat normally after a few weeks; a small number notice looser motions after very fatty meals initially, which usually settles.
How do I know if my abdominal pain is appendicitis?
Classically it starts around the navel and shifts to the right lower abdomen, with nausea, loss of appetite and fever. But patterns vary, especially in children and the elderly. Persistent worsening abdominal pain should be examined rather than self-treated.
Are piles always treated with surgery?
No. Early piles respond to fibre, fluids, toilet-habit correction and medicines. Procedures are advised for persistent bleeding or prolapsing piles. Importantly, bleeding is evaluated properly first — not every bleed is piles.
What is laparoscopic surgery and is it better?
Laparoscopy uses small cuts and a camera instead of one large incision. For suitable cases it means less pain and faster recovery. It is not automatically right for every patient — your surgeon will recommend the approach that is safest for your situation.
How long will I stay in hospital after hernia surgery?
Many laparoscopic hernia repairs are day-care or overnight-stay procedures. Open repairs and patients with other medical conditions may stay a little longer. You will get a clear estimate at the planning stage.
When can I return to work after surgery?
Desk work is often possible in 1–2 weeks after laparoscopic surgery. Physical labour and heavy lifting need longer — typically 6 weeks or more after hernia repair. Your discharge summary will specify this for your operation.
Is surgery safe if I have diabetes or blood pressure?
Yes, with proper preparation. Sugar and BP are optimised before elective surgery, and anaesthesia is planned accordingly. This is exactly why the pre-anaesthesia check-up exists — do not skip it.
Videos & reels
General Surgery videos
Short videos shared by the hospital about this service.
▶
Videos coming soon
The hospital can add service-related YouTube or Instagram videos in the admin panel.
Videos are provided for general information. They do not replace medical advice, diagnosis or treatment.
Help us improve this page
Share feedback about this service information
Your message is sent privately to the hospital team and is not published as a review. Please do not include patient records, test results or other sensitive medical details.
For appointments, use the appointment form. For urgent medical help, call 112 or go to the nearest emergency department.
Related services
Explore related care
Colorectal Surgery
Evaluation of conditions involving the colon, rectum and related structures.